
TL;DR:
- Poor hygiene in clinics and childcare centers increases infection risks and business liabilities.
- Best practices include frequent high-touch surface cleaning, TGA-approved disinfectants, and traceability testing.
- Going beyond minimum standards and building hygiene into culture reduces outbreaks and enhances trust.
Most business owners running a clinic or childcare centre in East Melbourne assume that if a space looks clean, it is clean. That assumption carries real risk. HAIs affect 7% of patients in developed countries, and many of those infections trace back to overlooked surfaces, inconsistent cleaning schedules, and products that simply do not meet the mark. This guide cuts through the noise and gives you a practical, evidence-based roadmap for lifting hygiene standards in your facility. Whether you manage a GP clinic, a specialist practice, or a childcare centre, what follows will help you protect your clients, your staff, and your business.
Table of Contents
- The real risks behind poor facility hygiene
- What world-class hygiene looks like: Best practices for medical facilities
- Key challenges and expert solutions: Pitfalls, edge cases, and what most guides miss
- Practical steps for East Melbourne SMBs: Tailoring hygiene to your facility
- A fresh perspective: Why going ‘above and beyond’ is now essential, not optional
- Find your hygiene partner: Cleaning solutions for East Melbourne facilities
- Frequently asked questions
Key Takeaways
| Point | Details |
|---|---|
| Contamination risks | Poor hygiene puts patients and staff at direct risk of avoidable infections. |
| Best-practice cleaning | Using high-frequency cleaning, TGA-approved disinfectants, and proper techniques lowers HAI rates. |
| Monitoring matters | Regular quality checks like ATP testing and checklists ensure high standards are met. |
| Practical application | Local SMBs can reduce liability and improve safety with smart, evidence-based hygiene routines. |
The real risks behind poor facility hygiene
Poor hygiene in a medical or childcare setting is not just an aesthetic problem. It is a clinical one. When cleaning is inconsistent or inadequate, pathogens accumulate on surfaces, spread to hands, and then to patients or children. The importance of medical cleaning cannot be overstated when you consider how quickly a single contaminated surface can seed an outbreak across an entire ward or room.
Environmental hygiene correlates directly with HAI rates, with high colony counts on surfaces increasing infection risks measurably. This is not a theoretical concern. It plays out in clinics every week. High-touch surfaces such as door handles, light switches, taps, and examination tables are the primary vectors. Staff hands are equally implicated, particularly when hand hygiene protocols are not reinforced by a rigorous cleaning programme.
The business consequences are just as serious as the clinical ones. Consider the following data:
| Risk factor | Potential consequence |
|---|---|
| Inconsistent surface cleaning | Elevated HAI rates, patient complaints |
| Non-compliant disinfectants | Regulatory penalties, licence risk |
| Poor traceability | Failed audits, legal liability |
| Infrequent high-touch cleaning | Rapid pathogen spread |
The financial exposure for small to medium business owners is significant. A single outbreak can trigger a formal investigation, damage your reputation with referral networks, and expose you to negligence claims. Cleaning quality traceability in sterilisation centres improved compliance from 78.5% to 96.4% and reduced HAIs by 42.6%. That is not a marginal gain. That is the difference between a facility that passes audits and one that does not.
Key contamination vectors to address in any facility include:
- High-touch surfaces: door handles, light switches, reception counters, taps
- Staff hands: the most common route for cross-contamination
- Shared equipment: blood pressure cuffs, stethoscopes, keyboard surfaces
- Waiting areas: chairs, children’s toys, magazines, and pens
- Waste and linen handling: incorrect disposal spreads pathogens rapidly
Understanding these vectors is the first step. Enhancing patient safety through structured cleaning is the practical response, and it starts with knowing what world-class hygiene actually looks like.
What world-class hygiene looks like: Best practices for medical facilities
There is a meaningful gap between meeting the legal minimum and practising genuine best-practice hygiene. Many facilities in East Melbourne tick the compliance boxes but still fall short of the standards that protect patients and children in real-world conditions.
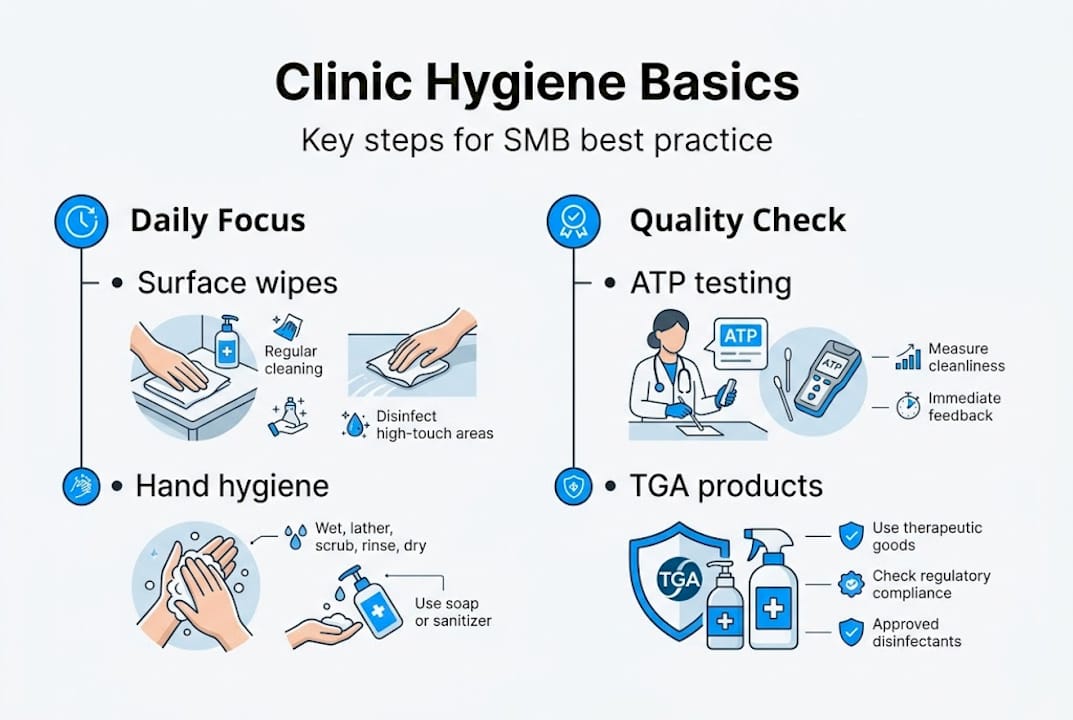
The foundation of any reliable cleaning programme starts with a few non-negotiable principles drawn from WHO cleaning principles: always clean before you disinfect, work top-to-bottom and from clean to dirty zones, use colour-coded cloths and mop heads to prevent cross-contamination, and avoid using spray mists that aerosolise pathogens.
| Practice level | What it looks like |
|---|---|
| Minimum compliance | Daily clean, basic products, no traceability |
| Industry best practice | 3-4x daily high-touch cleans, TGA-approved products, ATP testing, audit logs |
High-touch surfaces in a busy clinic or childcare centre should be cleaned three to four times daily, not once. This is not excessive. It reflects actual pathogen accumulation rates in high-traffic environments. Enhanced cleaning in ICUs reduced MRSA environmental contamination by 38% and on staff hands by 74%. The same principle applies at scale in any clinical or care setting.

TGA-approved disinfectants are essential. These products have been assessed by the Therapeutic Goods Administration for safety and efficacy, meaning they are proven to work against the specific pathogens relevant to your setting. Using unverified products is a compliance risk and a patient safety risk.
Traceability matters just as much as the cleaning itself. ATP (adenosine triphosphate) testing measures organic residue on surfaces and gives you an objective, real-time indicator of cleaning quality. Regular audits and cleaning logs provide the documentation trail you need if your facility is ever inspected.
Pro Tip: Ask your cleaning provider to supply ATP test results alongside their standard service reports. If they cannot provide this, that tells you something important about their standards.
For more detail on building a structured approach, the facility sanitation tips and the sanitation compliance guide are practical starting points for East Melbourne operators.
Key challenges and expert solutions: Pitfalls, edge cases, and what most guides miss
Even facilities with solid routine cleaning programmes can be caught off guard by edge cases. Outbreak scenarios, monitoring gaps, and over-reliance on technology are three areas where local operators consistently struggle.
Outbreak protocols require a different gear entirely. When a notifiable illness or cluster event occurs, standard cleaning is not enough. Terminal cleaning protocols require the use of sporicidal agents, increased cleaning frequency, and a documented response plan. Terminal cleaning means treating every surface in an affected space as potentially contaminated, not just the obvious ones.
Here are the four most common pitfalls we see in East Melbourne facilities:
- Under-cleaning staff hands and high-touch surfaces. Hand hygiene reminders are posted everywhere, but actual compliance is rarely monitored. Pair hand hygiene with surface cleaning frequency for real impact.
- Inconsistent scheduling. Cleaning that happens “when someone has time” is not a cleaning programme. Fixed schedules with accountability are essential.
- Over-relying on no-touch technology. UV-C disinfection and electrostatic sprayers are useful tools, but they do not replace manual cleaning. Organic matter on surfaces blocks UV light and reduces efficacy. A blended approach is always more effective.
- Skipping monitoring between outbreaks. Routine bacteriological monitoring is not always needed outside of outbreaks, but regular quality checks using ATP testing and visual audits keep your programme honest.
“The facilities that handle outbreaks best are the ones that already have strong routine protocols. They simply escalate what they already do well.”
Pro Tip: Review your cleaning procedures compliance documentation before your next audit. Gaps in your records are often flagged before gaps in your actual cleaning.
For a structured approach to audit readiness, the cleaning compliance checklist is a useful tool. Pair it with the environmental hygiene research to understand the evidence behind each requirement.
Practical steps for East Melbourne SMBs: Tailoring hygiene to your facility
Knowing the theory is one thing. Applying it to a busy GP practice or a childcare centre in East Melbourne is another. Here is how to translate research into action.
Start by honestly assessing your current cleaning provider. Do they use TGA-approved products? Can they provide ATP test results? Do they have documented cleaning schedules with sign-off logs? If the answer to any of these is no, you have a gap worth addressing.
For childcare centres specifically, the NHMRC Staying Healthy guidelines are the benchmark. They stress cleaning, exclusion of ill children, and immunisation as the three pillars of infection control. Your cleaning programme needs to align with all three, not just the visible cleaning component.
It is also worth noting that globally, 50% of healthcare facilities lack piped water and 33% lack improved sanitation, which underscores how reliable cleaning infrastructure reduces infection risk. East Melbourne facilities are fortunate to have the resources. The question is whether they are being used well.
Here is a practical checklist for SMB operators reviewing their hygiene programme:
- Medical facilities: Confirm NSQHS Standard 3 compliance, verify TGA-approved product use, request traceability logs, schedule ATP testing quarterly
- Childcare centres: Align with ACECQA hygiene requirements, follow NHMRC exclusion and cleaning guidelines, ensure nappy change and food prep areas are cleaned separately with colour-coded equipment
- Both settings: Require written cleaning schedules, confirm staff training records, review incident logs for any hygiene-related complaints
Pro Tip: When interviewing a new cleaning provider, ask them to walk you through their outbreak response protocol. A provider who cannot answer that question clearly is not ready for your facility.
The essential clinic cleaning steps and practical cleaning standards pages offer East Melbourne-specific guidance for getting this right.
A fresh perspective: Why going ‘above and beyond’ is now essential, not optional
There is a persistent belief in the SMB sector that passing an audit is the goal. It is not. Audits measure a moment in time. Infections happen continuously.
The clinics and childcare centres that genuinely protect their clients are not the ones scrambling to meet minimum standards before an inspection. They are the ones that have built hygiene into their operational culture. That means regular monitoring, proactive provider reviews, and a willingness to invest in better systems before something goes wrong.
Here is the uncomfortable truth: the cost of going above and beyond is far lower than the cost of a single outbreak, a failed audit, or a negligence claim. The facilities that treat meeting sanitation guidelines as a floor rather than a ceiling are the ones that earn client trust, retain good staff, and sleep well at night. In 2026, with infection risks evolving and audit standards tightening, the minimum is genuinely the riskiest place to be.
Find your hygiene partner: Cleaning solutions for East Melbourne facilities
If this article has prompted you to take a closer look at your current cleaning arrangements, that is a good instinct to follow. At 360 Cleaning Solutions, we work with medical clinics and childcare centres across East Melbourne to deliver hygiene programmes that go well beyond surface-level cleaning. Our teams use TGA-approved products, maintain full traceability logs, and are trained in both NSQHS and ACECQA compliance requirements. Whether you need a structured medical sanitation guide to benchmark your current provider or are looking for dedicated childcare cleaning services, we can help. Start with our facility cleaning checklist to identify where your programme stands today.
Frequently asked questions
What are the most common sources of infection in medical facilities?
Staff hands and high-touch surfaces are the primary vectors for infection spread, which is why frequent, targeted cleaning of these areas is non-negotiable in any clinical setting.
How often should high-touch surfaces be cleaned in clinics?
Best practice is to clean high-touch points three to four times daily, with higher frequency in busy areas such as waiting rooms and treatment rooms where patient turnover is constant.
What are TGA-approved disinfectants and why should I ask for them?
TGA-approved disinfectants meet Australian regulatory standards for safety and efficacy, and using compliant products protects both your patients and your facility from regulatory risk.
Is routine lab testing necessary to monitor cleaning quality?
Routine bacteriological monitoring is not always required outside of outbreak situations, but ATP testing and regular visual audits provide a practical and effective alternative for ongoing quality assurance.
Recommended
- Medical facility sanitation: essential guide for 2026
- Sanitation in medical offices: protect patients, stay compliant
- Top medical facility sanitation tips for safer clinics
- 7 Medical Clinic Cleaning Essentials for Safer Workplaces
- Outdoor disinfection: Evidence-based guidance for Citrus County – white-diamond-pressure