
Medical waste cleaning procedures are defined as systematic, evidence-based protocols for safely containing, cleaning, disinfecting, and disposing of biohazardous materials in healthcare settings. These procedures sit at the intersection of infection control, environmental compliance, and staff safety. Health and safety officers who apply them correctly protect patients, staff, and the broader community. Australian regulations place primary responsibility at the state level, so understanding both national standards and your specific state’s requirements is non-negotiable. 360 Cleaning Solutions works alongside healthcare facilities to support compliant, consistent cleaning workflows that meet 2026 standards.
What are the key steps in medical waste cleaning procedures?
Effective biohazard spill management follows a strict sequence. Skipping or reordering steps does not just reduce efficacy. It actively creates new contamination risks.
Step 1: Contain the spill and don PPE

Stop the spread before touching anything. Place absorbent material around the perimeter of the spill, then put on gloves, a gown, eye protection, and a mask before making contact. PPE is only protective when worn correctly from the start.
Step 2: Remove organic matter before disinfecting
Disinfectants cannot inactivate pathogens hidden beneath organic debris. Use a detergent solution to physically remove blood, tissue, or fluid first. This step is the one most often skipped, and skipping it renders the disinfection step useless.
Step 3: Apply an EPA-registered disinfectant at the correct dilution
For large blood or body fluid spills, use a bleach solution at a 1:10 dilution ratio. For smaller spills, a 1:100 ratio is appropriate. The disinfectant must remain wet on the surface for a minimum contact time of 10 minutes. Wiping it away before that point defeats the purpose entirely.
Step 4: Collect and bag all contaminated materials
Place all used cloths, absorbent materials, and disposable PPE into correctly labelled biohazard bags. Seal the bags securely. Double-bagging is required when the outer surface of the first bag is visibly contaminated.
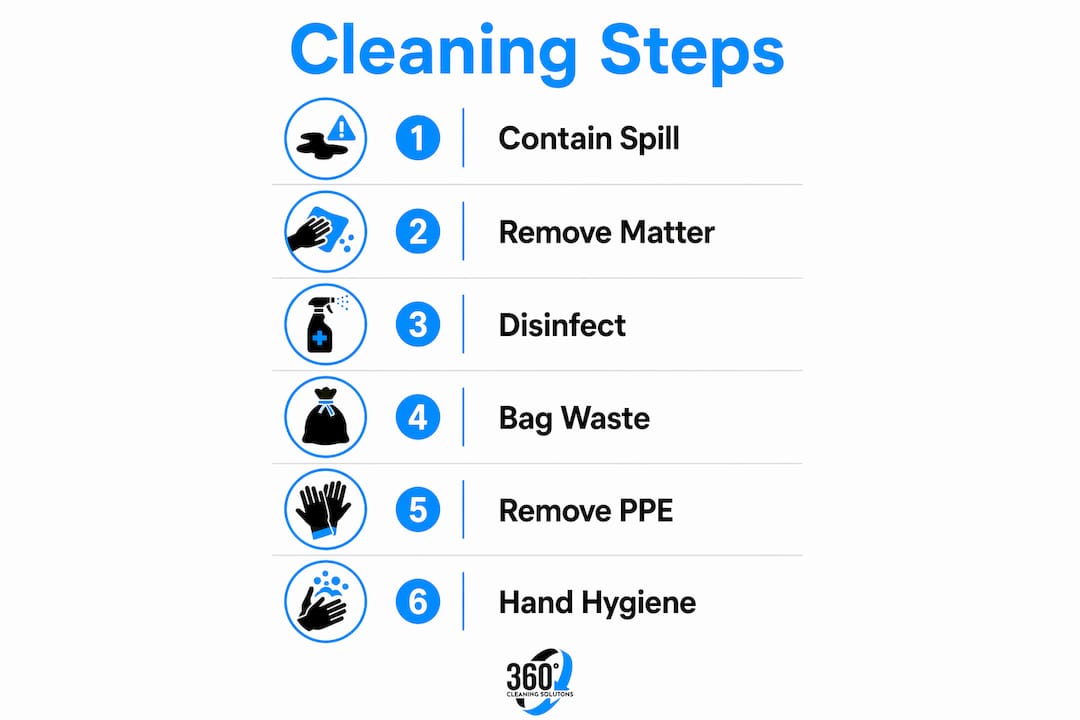
Step 5: Remove PPE correctly
Incorrect PPE removal is one of the most common causes of re-contamination. Peel gloves inside-out away from the body. Remove the gown without touching the outer surface. Dispose of all items in a biohazard bag immediately.
Step 6: Perform hand hygiene
Wash hands with soap and water for at least 20 seconds after removing PPE, even if gloves were worn throughout. Alcohol-based hand rub is not a substitute when hands are visibly soiled.
Pro Tip: Use colour-coded cleaning cloths and mops for different zones. A colour-coded system is the most effective low-cost intervention to prevent cross-contamination between clinical areas.
Cleaning must always follow a linear sequence from clean to dirty surfaces. Starting in a contaminated zone and moving to a clean one spreads pathogens rather than removing them. This principle applies to both spill response and routine room cleaning.
How is medical waste segregated, stored, and prepared for disposal?
Segregation at the point of generation is the single most important step in the entire waste management chain. Mixing waste types after the fact is costly, time-consuming, and often non-compliant.
Waste categories and container requirements
- Clinical and infectious waste: Soft clinical waste such as dressings and gloves goes into yellow biohazard bags. Sharps go into rigid, puncture-resistant containers approved for that purpose.
- Sharps containers: Fill to no more than 75% capacity before sealing. Overfilled containers are a leading cause of needlestick injuries.
- Pharmaceutical waste: Segregate expired or unused medications into designated pharmaceutical waste containers. These require separate disposal pathways from clinical waste.
- Non-hazardous waste: Items that look clinical but are not contaminated do not always require biohazard disposal. Over-classification of waste is common and drives up costs unnecessarily. However, never discard potentially hazardous-looking items as general rubbish.
Storage and labelling requirements
All containers must be clearly labelled with the waste type, the generating facility, and the date of sealing. Storage areas must be locked, ventilated, and inaccessible to unauthorised personnel. Waste must not be stored beyond the timeframes specified by your state environmental agency.
Approved disposal methods
| Method | Waste type | Outcome |
|---|---|---|
| Autoclaving | Infectious soft waste | Steam sterilisation before landfill |
| Shredding | Treated solid waste | Volume reduction before disposal |
| Incineration | Pharmaceutical, anatomical | High-temperature destruction |
Autoclaving and shredding together reduce biohazardous waste volume by approximately 70% before landfill disposal. That reduction matters both for cost and for environmental impact. Facilities that segregate waste at the source also reduce their carbon footprint, aligning waste management with climate resilience goals.
For guidance on building these workflows into your facility’s daily operations, the medical facility sanitation guide from 360 Cleaning Solutions covers 2026 compliance requirements in detail.
What regulations and standards govern medical waste in Australia?
Medical waste regulation in Australia is primarily state-governed. There is no single federal framework that covers all aspects of clinical waste management. Health and safety officers must consult their specific state environmental protection authority and health department for permitting, documentation, and transport requirements.
Key regulatory obligations include:
- State EPA permits: Most states require facilities generating clinical waste above a threshold volume to hold a current permit. Permit conditions vary significantly between New South Wales, Victoria, Queensland, and other jurisdictions.
- Documentation and manifests: Waste transport must be accompanied by a consignment authorisation or manifest. This creates an auditable chain of custody from generation to final disposal.
- Staff training records: Regulators expect documented evidence that all staff who handle clinical waste have received appropriate training. Training records must be current and accessible during audits.
- Incident reporting: Spills, needlestick injuries, and disposal breaches must be reported through the facility’s incident management system and, in some cases, to the relevant state authority.
- Audit readiness: Internal audits should be conducted at least annually. External audits by state regulators can occur without prior notice.
Non-compliance carries serious consequences. Penalties include fines, licence suspension, and in severe cases, criminal liability for responsible officers. Beyond legal risk, a single compliance failure can trigger a public health investigation that disrupts facility operations for weeks.
The medical cleaning checklist for 2026 compliance provides a practical audit tool aligned with current state requirements.
Pro Tip: Keep a compliance register that maps each regulatory obligation to the staff member responsible, the frequency of review, and the date of last verification. This single document can significantly reduce audit preparation time.
What are common challenges in implementing waste cleaning procedures?
The gap between written policy and daily practice is where most compliance failures occur. Health and safety officers who understand the common failure points can design systems that close that gap.
The most frequent problems
- Improper disinfectant use: Staff dilute products incorrectly, apply them to surfaces still covered in organic matter, or wipe them away before the contact time has elapsed. All three errors result in surfaces that appear clean but remain contaminated.
- PPE misuse: Gloves are worn for too long, used across multiple zones, or removed incorrectly. Each of these behaviours transfers contamination rather than containing it.
- Waste misclassification: Both over-classification and under-classification create problems. Proper waste segregation reduces operational costs by avoiding unnecessary biohazard processing of non-contaminated items.
- Inconsistent colour-coding: Colour-coded systems only work when every staff member follows them every time. A single mop used in the wrong zone can spread contamination across an entire ward.
Strategies that work
Checklists reduce reliance on memory and make compliance visible. A laminated spill response checklist posted in every clinical area costs almost nothing and measurably improves adherence. Pair checklists with regular competency assessments rather than one-off training sessions.
Linear cleaning sequences, moving from the cleanest areas to the most contaminated, must be built into the physical workflow. This means starting at the far end of a corridor and working toward the exit, not the reverse. The sequence should be documented in the cleaning protocol and reinforced during every staff induction.
For biohazard cleaning safety in commercial and healthcare settings, the principle of clean-to-dirty sequencing applies equally to routine maintenance and emergency spill response.
Sustainable waste management practices also reduce long-term costs. Correct segregation at the source means less waste enters the expensive biohazard stream. Facilities that treat sustainability as a compliance issue rather than an optional extra consistently outperform those that do not.
Key takeaways
Effective medical waste management requires correct sequencing, proper disinfectant use, strict segregation, and state-specific regulatory compliance working together as a single system.
| Point | Details |
|---|---|
| Clean before disinfecting | Remove organic matter with detergent before applying any disinfectant to ensure it works. |
| Respect contact times | EPA-registered disinfectants require a minimum 10-minute dwell time on surfaces. |
| Fill containers to 75% only | Overfilled sharps containers cause needlestick injuries and breach compliance requirements. |
| Segregate waste at the source | Correct classification at the point of generation reduces cost and environmental impact. |
| Know your state’s rules | Australian medical waste regulation is state-governed; consult your local EPA for current requirements. |
Why the cleaning sequence matters more than the products you use
After years of working across healthcare and commercial cleaning environments, the pattern I keep seeing is the same. Facilities invest heavily in premium disinfectants and then apply them incorrectly. They buy the right product, skip the detergent step, and wonder why infection rates do not improve.
The sequence is the protocol. A hospital-grade disinfectant applied to a surface covered in blood or tissue fluid does nothing useful. The organic matter physically shields the pathogen from the active ingredient. This is not a theoretical risk. It is the mechanism by which healthcare-associated infections persist in well-resourced facilities.
Colour-coding is similarly underestimated. I have seen facilities with detailed written protocols and no colour-coded equipment. Staff make reasonable decisions in the moment, and those decisions spread contamination. A red mop for the bathroom and a blue mop for the ward is not bureaucracy. It is the difference between a clean surface and a contaminated one.
The regulatory landscape is also shifting. State EPAs are increasing audit frequency and tightening documentation requirements. The facilities that will manage this well are the ones building compliance into daily habit now, not scrambling to catch up when an inspector arrives.
My strongest recommendation is this: audit your cleaning sequence before you audit your products. The sequence is almost always where the problem lives.
— Jonathan
How 360 Cleaning Solutions supports healthcare cleaning compliance
Healthcare facilities need cleaning partners who understand the difference between routine office hygiene and clinical-grade sanitation. 360 Cleaning Solutions brings structured, compliance-focused cleaning workflows to medical and commercial environments across East Melbourne.
The team at 360 Cleaning Solutions applies documented cleaning protocols and staff training practices that align with current waste management and sanitation requirements. Services are delivered after hours with no lock-in contracts, minimising disruption to clinical operations. For facilities that need a reliable partner to support their sanitation and compliance obligations, the office cleaning workflow guide outlines how structured cleaning systems translate directly into safer, more compliant workplaces. Contact 360 Cleaning Solutions to discuss a cleaning programme tailored to your facility’s requirements.
FAQ
What is the correct bleach dilution for a blood spill?
Use a 1:10 bleach-to-water ratio for large blood spills and a 1:100 ratio for small spills. The disinfectant must remain on the surface for a minimum of 10 minutes to be effective.
How full should a sharps container be before sealing?
Sharps containers must be sealed when they reach 75% capacity. Filling beyond this point increases the risk of needlestick injuries and breaches waste handling compliance requirements.
Who regulates medical waste disposal in Australia?
Medical waste regulation in Australia is primarily state-governed. Health and safety officers must consult their specific state environmental protection authority for current permitting, documentation, and transport requirements.
Why must surfaces be cleaned with detergent before disinfecting?
Disinfectants cannot penetrate organic matter such as blood or tissue fluid. Detergent cleaning removes that debris first, allowing the disinfectant to make direct contact with pathogens and inactivate them.
How long should hand washing take after handling medical waste?
Staff must wash hands with soap and water for at least 20 seconds after removing PPE, even when gloves were worn throughout the cleanup process.